In recent years, few studies have been conducted on the hierarchical assisted diagnosis of cervical lesions and most of them are still insufficient and their clinical significance is extremely limited. Based on this, this paper designs densely contextual transformer networks (DCTNet) to diagnose cervical lesions. DCTNet benefits from its internal DCT module and multi-spectral channel attention (MSCA) module to diagnose cervical lesions efficiently. First, the DCT module effectively combines the ability of the transformer to capture global contextual information with the ability of the convolutional neural networks to capture neighboring local contextual information, which enhances the visual representation of the network. Second, the MSCA module can effectively use the information of more frequency components to enrich the feature representation ability of the network. The results show that under the same research conditions, the diagnostic performance of DCTNet is generally superior to other current diagnostic methods; the area under the curve value is 0.8332. While the clinical diagnostic performance reaches the level of advanced physicians, close to the expert physicians, with excellent auxiliary diagnostic performance. Therefore, DCTNet can effectively alleviate the pressure on physicians in resource-poor areas.
1.Introduction
According to the global cancer statistics report released by the International Agency for Research on Cancer of the World Health Organization, the number of new cases of cervical cancer in the world reached 604,127 and the number of deaths was 341,831, which ranked fourth in the incidence and mortality of female cancers (Sung et al., 2021). At the same time, the incidence and mortality of cervical cancer are gradually increasing and patients are getting younger. Currently, a quarter of the affected population are young women aged 20–39 (Siegel et al., 2020, 2023), so early prevention and diagnosis of cervical cancer are particularly important. Studies have shown that the main cause of cervical cancer is persistent infection with high-risk human papillomavirus (Bouvard et al., 2009) and it usually takes years or even decades for patients to develop cervical cancer from infection. This is the main cause of cervical cancer, which is called cervical intraepithelial neoplasia (CIN). This period is called CIN, which can be categorized into CIN1, CIN2 and CIN3 according to the degree of clinical lesions (Safaeian et al., 2007). In clinical practice, CIN1 is often referred to as low-grade squamous intraepithelial lesion (LSIL), CIN2 and CIN3 are collectively referred to as high-grade squamous intraepithelial lesion (HSIL).With conservative observation and timely treatment, most lesions in LSIL patients can be cleared by the autoimmune system. However, if it progresses to HSIL or even higher stages, the survival rate drops significantly by 20%-50% (Pfaendler et al., 2015; Xu et al., 2017). Although cervical cancer is currently the only malignant tumor that can be prevented by the human papillomavirus (HPV) vaccine (Olaf and Sigrid, 2015; Falcaro et al., 2021). Due to the high price of the vaccine and regional differences, its prevalence is not high enough to meet the needs of most women in prevention and treatment (Dong et al., 2021). Therefore, it is of great significance to carry out large-scale screening for cervical lesions in the female population so as to greatly reduce the morbidity and mortality of patients through early detection and diagnosis.
Currently, the main cervical cancer screening techniques include Pap smear (pap), HPV testing, thinprep cytologic (TCT) testing and colposcopic visualization (Cohen et al., 2019). The former techniques are relatively complex and expensive and require high facilities, while colposcopy has the advantages of being simple to operate, inexpensive and relatively noninvasive, making it the first choice for cervical cancer screening (Waxman et al., 2017). However, it is easily affected by the lighting environment, individual differences of the subjects. The accuracy of the test is highly dependent on the experience and expertise of the clinician, so its disadvantage is the strong subjectivity of the test process. At the same time, in large-scale group screening, the screening efficiency of physicians is reduced and the possibility of leakage and misdiagnosis is inevitably increased.
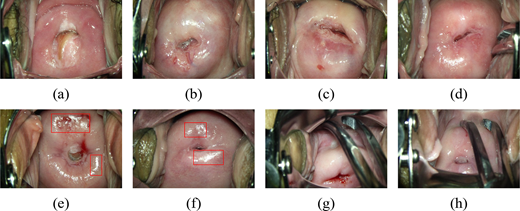
In recent years, the use of artificial intelligence technology to make up for the deficiencies in cervical cancer screening has become a hot research topic in the field of computer-aided diagnosis. That is, cervical cancer images collected by colposcopy imaging technology are used for automatic identification and auxiliary diagnosis, which realizes the automation of clinical cervical cancer screening to reduce the workload of doctors and reduce missed detections and false detections. Clinically, it is divided into four categories according to the degree of lesions, namely, normal, LSIL, HSIL and Cancer. However, the visual similarity between the images of each category is extremely high [see Figures 1(a)-(d)], which narrows the scope of each category. The inter-class variance between classes and the image itself also have light reflection [see Figures 1(e) and (f)], and occlusion [see Figures 1(g) and (h)], which increases the risk of cervical cancer and diagnostic challenges.
2.Related work
Benefiting from the powerful feature extraction capability of deep learning (LeCun et al., 2015), this technology has led to a wide range of applications in the field of cervical lesion diagnosis. Examples include the use of Pap smear images for cervical cancer diagnosis (Pirovano et al., 2021; Rahaman et al., 2021; Liu, 2022a; Attallah, 2023; Pramanik et al., 2023), optical coherence tomography (OCT) images for diagnosis (Wang et al., 2023) and colposcopy images for assisted diagnosis. Currently, deep convolutional neural networks (CNN) have achieved excellent comprehensive performance compared to both manual diagnosis by clinical colposcopists and cervical lesion diagnosis methods based on traditional image processing techniques. Table 1 summarizes recent research on methods for cervical lesion diagnosis using colposcopic images. Zhang et al. (2020) proposed a pretrained densely connected convolutional network architecture that, through fine-tuning strategies, enabled the model to achieve performance comparable to that of advanced practitioners. Their team subsequently developed a novel data augmentation strategy to optimize model output by integrating and fusing multiple CNN decision features, which further improved the accuracy of cervical lesion diagnosis and enhanced the applicability of pre-cancer screening (Luo et al., 2020). Although their study achieved promising results, it was limited to binary classification (dichotomous diagnosis), which provides limited clinical utility for comprehensive patient management.
Saini et al. (2020) proposed ColpoNet, a cervical cancer classification method based on DenseNet architecture, achieving superior results compared to other deep learning models. Similarly, Cho et al. (2020) developed a classification method based on the lower anogenital squamous terminology (LAST) system to categorize lesions as either high-risk or low-risk using deep learning approaches. Despite promising performance metrics, both studies (Saini et al., 2020; Cho et al., 2020) were constrained by their binary classification frameworks, limiting their clinical applicability. In contrast, Aina et al. (2021) optimized fine-tuned CNNs through mixed-precision training combined with advanced techniques such as data augmentation, 1-cycle policy and discriminative fine-tuning. Their approach achieved five-class classification on a limited dataset with an accuracy of 96.3% and sensitivity of 95%, demonstrating significant potential for clinical assistance. Similarly, Liu et al. (2021a; 2021b) mapped lesion probability distributions for each patient using a ResNet-based framework and fused clinical features to construct a combined diagnostic model. Their results were compared against diagnostic assessments from both senior and junior colposcopists, with the model achieving performance comparable to the senior specialist. While their work demonstrated that the fusion of clinical features and CNNs produces superior results to either approach alone, this method requires manual filtering of clinical features, preventing it from being a true end-to-end solution and limiting its practical clinical deployment. Additionally, their exclusion of images with cervical abnormalities and occlusions to ensure image clarity further restricts the model’s applicability in real-world clinical scenarios.
In the field of object detection, networks capture deep features from numerous images through nonlinear operations, after which candidate target regions obtained through classification enable precise detection of regions of interest. This approach has provided new perspectives for cervical lesion diagnosis, with research based on faster region-based convolutional neural networks (Faster R-CNN) gaining prominence (Ren et al., 2017). The primary advantage of this architecture is its implementation of region proposal networks to identify target regions of interest, enabling rapid and efficient detection. Building on this foundation, Elakkiya et al. (2022) proposed the faster small object detection neural networks-generative adversarial networks (FSOD-GAN) for colposcopic image analysis. Their approach automatically detects cervical abnormalities using a combination of Faster R-CNN and generative adversarial networks (GANs), performing binary normal/abnormal classification. In contrast to this work, other literature (Bai et al., 2020; Li et al., 2020) has pursued detection through specialized CNN structures. Bai et al. (2020) achieved detection of lesion regions above the CIN2 threshold by incorporating a feature recalibration mechanism into CNN architecture to enhance utilization of relevant features while suppressing noncontributory ones. Li et al. (2020), working with multi-frame time-lapse colposcopy images, developed a system that identifies LSIL+ lesion regions through a key frame feature encoding network combined with a feature fusion network. While innovative, these approaches remain insufficient for comprehensive clinical deployment due to their limited scope and binary classification frameworks. Another notable contribution comes from researchers who developed a novel feature augmentation mechanism incorporating a local bin excitation module to effectively detect HSIL regions. This work represents one of the first implementations of combined global and local feature augmentation mechanisms for cervical lesion detection tasks. However, similar to Li et al. (2020), this approach fails to address the detection of other lesion classes and consequently lacks broad clinical applicability.
Alternative approaches to cervical lesion diagnosis have emerged from multimodal data fusion perspectives (Chen et al., 2022a; Fu et al., 2022; Ma et al., 2022; Xu et al., 2023). Chen et al. (2022a) proposed a multi-modality (acetic and iodine) corresponding region fusion network (CRFNet) that detects HSIL lesion regions across both imaging modalities. Their method extracts feature maps and generates proposals within each modality before performing proposal shifting to obtain corresponding region features, ultimately fusing these features using a novel channel attention mechanism. Xu et al. (2023) developed a tri-visual image (saline, acetic, iodine) feature integration framework guided by clinical expertise. By learning and fusing features from all three visual image types of the same patient, their model achieved diagnostic performance comparable to expert physicians. However, their approach required preprocessing steps, including ROI region cropping and elimination of light reflection areas, limiting its clinical adaptability. Ma et al. (2022) adopted a different strategy by first segmenting lesion areas from dual-modality colposcopic images (acetic and iodine) using segmentation algorithms, then extracting color and texture features from these segmented regions and fusing them with clinical information (TCT results, HPV test outcomes, patient age) before final classification. Similarly, Fu et al. (2022) constructed separate deep learning models based on saline, acetic and iodine images using CNNs, then combined these results with cytology and HPV test outcomes to build a cross-modality integrated model using multivariable logistic regression (MLR). Their comprehensive approach achieved an impressive area under the curve (AUC) value of 0.921. However, like Ma et al. (2022), these methods rely heavily on clinical information integration and extensive data preprocessing, which compromises their clinical suitability and practical implementation potential in diverse healthcare settings.
To summarize, the current study has shortcomings. Compared with them, the study in this paper has the following advantages:
The categories of diagnosis are comprehensive, completely covering all categories of pre-cancerous cervix, which is more in line with the needs of the clinical environment.
No need to perform pre-processing operations such as cervical region cropping and light reflection region elimination on the data, which is more in line with the needs of clinical applications.
Realize the ability combination of transformer and CNN and use it to design DCTNet, with stronger model ability and fewer parameters and calculations, which is more in line with the needs of a real clinical environment.
3. Methodology
3.1 Method overview
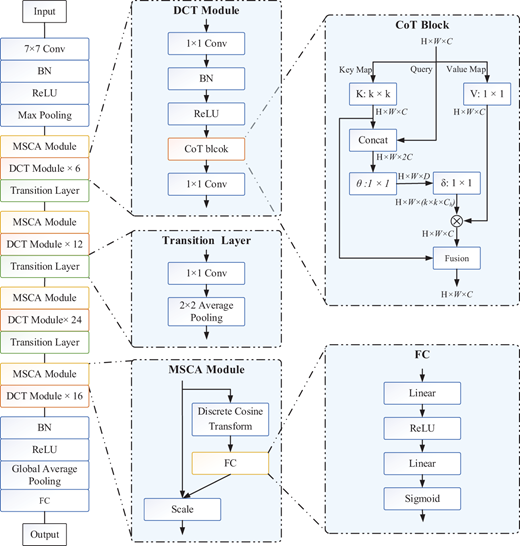
DCTNet can effectively diagnose cervical lesions by designing DCT module and MSCA module. The DCT module can effectively combine global context information with nearby local context information to enhance the visual representation capability of the network. Second, the MSCA module can effectively use more frequency component information to enrich the feature representation capabilities of the network. The overall framework of DCTNet is shown in Figure 2 and the detailed architecture is shown in Table 2. The components of DCTNet will be introduced in detail below.
3.2 Densely contextual transformer module
Many previous studies (Dosovitskiy et al., 2021; Liu et al. (2021a; 2021b) have demonstrated the potential of Transformers in the field of computer vision, primarily due to their self-attention mechanism. The advantage of this mechanism lies in its ability to effectively learn global information from an image, thereby partially addressing the issue of the limited receptive field in traditional CNNs. While the standard self-attention mechanism in Transformers can learn local relationships, it lacks this built-in spatial prior, treating the image as a set of patches. This can make it less sample-efficient for learning fundamental local patterns compared to CNNs.
For the diagnosis of cervical lesions, both global and local views are essential. A global perspective is crucial for identifying overall structural changes, while a local perspective is necessary for detecting subtle variations in specific regions. The morphological characteristics and progression of cervical lesions are reflected not only in local area changes but also in the broader structural context.
Therefore, we propose a network that effectively combines both neighborhood and global contextual information to enhance feature representation. To achieve this, we designed the DCT module, which integrates the transformer’s capability to capture global contextual information with the CNN’s strength in capturing neighboring local contextual information. This combination enhances the visual representation capabilities of the network, thereby improving the diagnostic accuracy and robustness when dealing with complex cervical lesion images.
As shown in the DCT module in Figure 2, drawing on the 3-layer structure of the Bottleneck block in ResNet (He et al., 2016), the DCT module also adopts a 3-layer architecture, consisting of convolution, self-attention and convolution operations. These correspond to BN–ReLU–1 × 1 conv, BN–ReLU–CoT block and BN–ReLU–1 × 1 conv, respectively. It is worth noting that while the original ResNet Bottleneck applies a convolution first, followed by BN (Ioffe and Szegedy, 2015) and ReLU (Glorot et al., 2011), we instead apply BN and ReLU prior to convolution. This design is motivated by findings in Huang et al. (2017), which suggest that performing BN and ReLU before convolution can improve computational efficiency.
In chain of thought (CoT) block, the input feature map is assumed to be . The keys, queries and values are denoted as , and , respectively, (Li et al., 2023). The CoT block first spatially performs a convolution operation on all neighbor keys (neighbor keys) within a grid to learn and obtain the static context information of the neighbor keys in the image. Afterwards, the static context information and queries are fused by Concat to obtain .
The attention matrix A is computed through two sequential 1 × 1 convolutional operation: and . Specifically: is a 1 × 1 convolutional layer followed by BN and a ReLU activation function, while is a 1 × 1 convolutional layer without BN or non-linear activation. Mathematically, this process is formalized as follows:
Here, represents the input feature tensor. Unlike traditional attention mechanisms that rely on pairwise query-key interactions, is learned directly from joint query-context representations, enabling it to capture spatial dependencies and contextual relationships more effectively. This design enhances the model’s ability to discriminate features by integrating global context into local attention computations, thereby improving feature learning robustness.
Next, by aggregating the attention matrix A and values V with contextual information, the dynamic contextual feature information between input images is obtained.
Finally, the static context and dynamic context are fused as the output of the CoT block through the attention mechanism (Li et al., 2019).
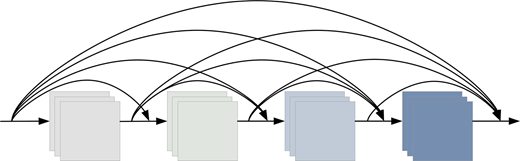
Meanwhile, we apply the dense connectivity pattern in the DCT module, i.e. connecting all the layers with each other, as shown in Figure 3. For the current layer, the feature mappings of all the previous layers can be used by it and the feature mappings of the layer itself will be used by all the layers behind it and such connectivity can significantly reduce the problems caused by gradient vanishing, enhance the transfer between features and focus on feature reuse and effectively save the amount of computation (Huang et al., 2017). On the other hand, it can also further combine the advantages of self-attention and convolution to achieve the combination of global and neighborhood information and enhance the network performance.
3.3 Multi-spectral channel attention module
Global average pooling (GAP) is often used in previous channel attention mechanisms and the use of GAP represents the use of information from the lowest frequency only and information from other frequencies is completely discarded (Hu et al., 2018). However, in reality the other frequencies contain a lot of useful information that should not be discarded. Therefore, more frequency components are introduced in the MSCA module to fully use the information (Qin et al., 2021).
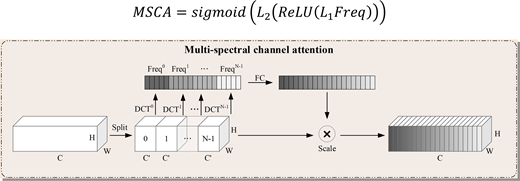
To compress the channel and use the information of other frequencies more conveniently, MSCA introduces more frequency components of the 2D discrete cosine transform (2D-DCT) to compress more information, which also includes the component of the lowest frequency, i.e. GAP. Assuming that the input feature map is X, X is first partitioned into N parts along the channel dimension to obtain and each part of X corresponds to the division of a 2D-DCT frequency component and the final result is the compression result of the channel attention:
where , and is the two-dimensional index of the frequency component corresponding to . is the compressed vector. When the entire operation is repeated N times, the entire compression vector is obtained through the concat fusion operation:
where is the obtained multi-spectral vector (multi-spectral vector).
Finally, the weights are obtained through the linear layer and the ReLU activation function and sigmoid function, as shown in the following equation, where and denote the first and second linear layers, respectively. The MSCA module obtains information about other frequencies in this way, which effectively enriches the feature representation (Figure 4).
3.4 Implementation details
All experiments in this paper are based on the implementation of PyTorch 1.7.1. DCTNet is trained using the stochastic gradient descent (SGD) optimizer, with the weight decay set to 0.0001 and the momentum set to 0.9. The initial learning rate is set to 0.002, which is gradually reduced to 0.0002 using a cosine annealing scheduler over the total number of training iterations (typically 100 epochs). The loss function is cross entropy loss, which is commonly used in multi-classification problems. For data preprocessing and augmentation, normalized using ImageNet statistics (mean = [0.485, 0.456, 0.406], std = [0.229, 0.224, 0.225]). Augmentations applied during training include random horizontal flipping (probability 0.5), random rotation (up to 10 degrees) and random cropping (with a padding of 4 pixels). No augmentations are applied during validation or testing. To ensure reproducibility, all experiments were conducted with a fixed random seed of 42, set via torch.manual_seed (42), np.random.seed (42) and random.seed (42). Results reported throughout the paper represent the mean across five independent runs with the same hyperparameters and seed initialization. The training convergence time is 48 ± 2 h on an NVIDIA GeForce RTX 2060 (with 6 GB VRAM, batch size = 32) and the average inference time is 50 ± 3 ms per sample (measured on the same GPU for 1000 test samples). Training the DCTNet model on an NVIDIA GeForce RTX 2060 involves substantial computational power, as noted above. Furthermore, inference speed is critical in clinical applications; the model’s performance makes it feasible for real-time clinical use. The source code, trained model weights and full experimental scripts will be publicly released upon publication to facilitate replication and further research.
4. Experiments
4.1 Dataset
The dataset used for the experiments in this paper was collected from the First Hospital of Quanzhou Affiliated to Fujian Medical University, the Second Hospital Affiliated to Fujian Medical University and Medical Center of Cervical Disease and Colposcopy Affiliated to Fujian Maternity and Child Health Hospital, with a total of 3,770 patients’ colposcopic image data, of which 1,344 cases of Normal, 1,354 cases of LSIL, 928 cases of HSIL and 144 cases of Cancer and the data were researched and used with the consent of the patients. The dataset was divided into training set, validation set and test set according to the ratio of 5:1:1 to ensure that the trained model has better generalization and robustness. The specific data distribution is shown in the table, the training set (consisting of 960 Normal, 968 LSIL, 664 HSIL and 102 Cancer cases) was used for model training, the validation set and test set (both consisting of 192 Normal, 193 LSIL, 132 HSIL and 21 Cancer cases) were used to evaluate and test the model performance. All patients contained pathologic diagnostic reports as the ground truth for model training and the size of each colposcopic image was 512 × 341 pixels (Table 3).
4.2 Evaluation indicators
To quantitatively analyze the performance of our model, the following evaluation metrics were chosen to be used, including ACC, macro positive predicted value (PPVMacro), macro sensitivity (SENMacro), macro specificity (SPECMacro), macro negative predictive value (NPVMacro), macro F1 (F1Macro) and AUC. F1Macro is calculated from PPV and SEN, while the AUC value is the area under the Receiver operating characteristic curve. It can well reflect the comprehensive performance of the classification of unbalanced data. The detailed definitions of each metric are shown in the table and higher values represent better performance. In our experiments, n denotes the number of colposcopic image categories (equal to four in our experiments) and n denotes the number of image categories (equal to four in our experiments). , respectively, represent the number of true positives, true negatives, false positives and false negatives of the i-th prediction result (Table 4).
4.3 Experimental results
In this subsection, we first compare DCTNet with current representative computer vision models and diagnostic methods for cervical lesions. Then, we compare the diagnostic performance of DCTNet with five different levels of clinicians on another dataset to evaluate the clinical utility that DCTNet brings. Finally, we performed an ablation study to analyze the impact of different attentional mechanism module structures on DCTNet, as well as the impact of using different settings in the four phases of the DCTNet backbone (res2 → res3 → res4 → res5).
4.3.1 Comparison with state-of-the-art methods.
We compare DCTNet with current representative computer vision models, including ResNet, ResNeXt, DenseNet, VoVNet, Vision Transformer, Swin Transformer and ConvNeXt, as well as Zhang et.al and Cho et al.'s cervical lesion diagnostic methods (LAST system and pre-trained DenseNet). To ensure a fair comparison, the outputs of all models were changed to four classifications and none of the data were pre-processed, as well as using the same training means and the same SGD optimization algorithm. Table 5 shows the comparison results. It can be seen that on our dataset, a shallower model with an appropriate increase in the number of layers can significantly improve the performance, although this increases the FLOPs and parameter, e.g. the ACC of ResNet-101 is 2.79% higher than that of ResNet-50. Instead, in more complex models, increasing the number of model layers produces a negative effect, which is particularly evident in DenseNet, where the ACC of DenseNet-201 is 2.61% lower than that of DenseNet-169. VoVNet, a variant form of DenseNet, achieves even worse results, which may be due to the fact that VoVNet eliminates the model’s dense connections and underutilizes the extracted features. On the other hand, almost all of the Transformer models achieved good results, with the shortcoming that the model parameter is much more than CNN and is more demanding for the equipment in the clinical environment.
Also from the results of each metric in Table 5, we can see that our model is overall better than the other models. Specifically, DCTNet achieves the best results in ACC, SPEC Macro and NPV Macro metrics, with ACC, SPEC Macro and NPV Macro reaching 58.55%, 84.31% and 85.07%, respectively, outperforming the best model ConvNeXt-B, by 0.37%, 0.07% and 0.66%. Furthermore, to address the issue of statistical robustness, we calculated the 95% confidence intervals (CI) for our key metrics and performed formal statistical tests. DCTNet achieved a macro accuracy of 58.55% (95% CI: 54.5% - 62.6%) and an AUC of 0.8332 (95% CI: 0.801–0.865). We compared DCTNet with the strongest baseline, ConvNeXt-B, using the DeLong test for AUC. The results indicated that the improvement in accuracy was not statistically significant (p > 0.05), which is expected given the small margin. However, the DeLong test showed no significant difference in AUC (p > 0.05), confirming that our model’s diagnostic discrimination ability is comparable to the state-of-the-art. Crucially, DCTNet achieves this comparable performance with only 14.5% of the FLOPs and 6.9% of the parameters of ConvNeXt-B. This substantial improvement in computational efficiency underscores the primary advantage and practical value of our proposed method.
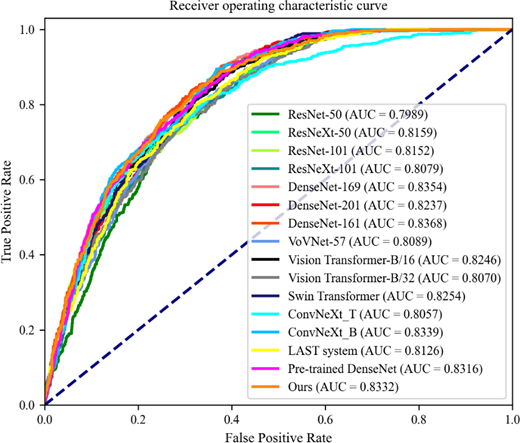
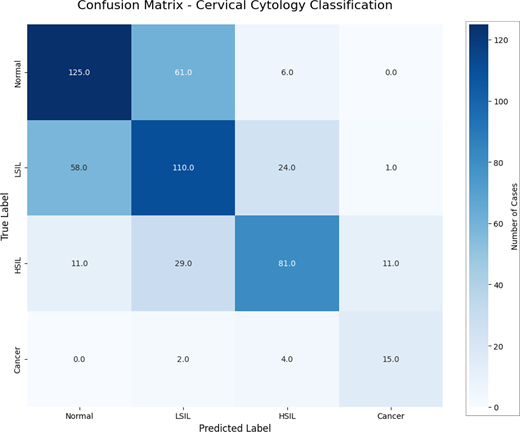
In addition, we show the ROC curves and AUC values of these models on the test set. As shown in Figure 5, the AUC value of our model is 0.8332, which is only 0.0036 lower than the best model, DenseNet-161, while our model is 5.57 G and 20.4 M less than DenseNet-161 in FLOPs and parameter, respectively, which means that we have achieved more than most of the models at the lowest cost. The confusion matrix in Figure 6 shows that the model accurately identifies both the normal and cancer classes, correctly classifying the majority of samples. In particular, the cancer class correctly identified 15 out of 21 samples, demonstrating high specificity. The main confusion occurred between the LSIL and HSIL classes and between Normal and LSIL. These results demonstrate that DCTNet has strong potential in the field of cervical lesion diagnosis and is more suitable for clinical settings.
4.3.2 Comparison with colposcopists.
In addition, we invited five clinical colposcopists of different expertise levels (including two expert physicians with over 15 years of experience, two senior physicians with 8–10 years of experience and one junior physician with 3 years of experience) to perform diagnosis on another dataset and compare it with DCTNet to verify the diagnostic performance and clinical significance of our model. To ensure methodological rigor, all physicians performed their evaluations independently in separate rooms using standardized digital interfaces. The reading sessions were conducted under strict blinding conditions where physicians were unaware of patient histories, final pathological diagnoses and other readers’ assessments. Each physician followed a standardized reading protocol that included a 10-minute familiarization period with the interface, followed by evaluation of the entire dataset at their own pace with no time constraints, though they were instructed to maintain typical clinical workflow speeds. Physicians documented their confidence levels for each diagnosis using a standardized 5-point scale. The dataset totaled image data from 102 patients, including 24 cases of normal, 24 cases of LSIL, 44 cases of HSIL and 10 cases of cancer.
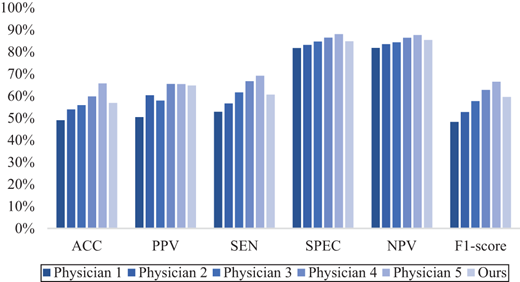
Table 6 shows the detailed comparison results; in terms of the ACC index, DCTNet outperformed three physicians (two senior and one junior) while showing slightly lower accuracy than the two expert physicians. Notably, both the clinicians and DCTNet demonstrated superior diagnostic performance for the cancer category compared to other categories, likely because cancerous lesions present more distinctive visual features that are more readily identifiable. The results also revealed considerable inter-observer variability among the five physicians, reflecting how diagnostic performance can be influenced by multiple factors, including clinical experience, personal diagnostic thresholds, attention to specific visual features and inherent decision-making tendencies.
Simultaneously, we calculated the average values of multiple metrics for each physician across the four diagnostic categories and visualized them as shown in Figure 7. Results demonstrated that DCTNet achieved a sensitivity of 72.5% and a specificity of 91.9% in identifying high-risk lesions (HSIL+). This high specificity indicates that the model effectively excludes the vast majority of low-risk patients, thereby preventing unnecessary patient anxiety and potential overtreatment. More importantly, the high negative predictive value (NPV) of 88.6% holds significant clinical value, as it indicates that when the model predicts low risk, this determination is highly reliable, allowing physicians to triage patients with greater confidence. Our analysis revealed that DCTNet’s overall diagnostic performance exceeded that of two senior physicians and one junior physician, approaching the level of expert physicians. This performance profile demonstrates DCTNet’s considerable potential in the field of cervical lesion diagnosis.
4.3.3 Ablation experiments.
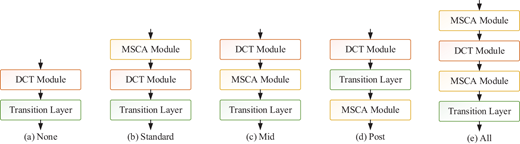
In this subsection, an ablation study is performed to better understand the effect of the MSCA module on DCTNet. The studies in this subsection all use the same parameters to ensure a balanced study and the only difference is the position of the MSCA module in DCTNet:
None: no MSCA module is added between the DCT module and the transition layer;
Standard: only the DCT module is added before the MSCA module;
Mid:add MSCA module in the middle of DCT module and transition layer;
Post: add MSCA module only after the DCT module; and
All: add MSCA module before and after the DCT module.
The specific positional relationships are shown in Figure 8, while we calculated the average values of the metrics of these five models for the four diagnostic categories and demonstrated them through Table 7.
To isolate the contribution of the MSCA module, we compared the Standard (DCTNet) model with the MSCA module and the None model with the MSCA module completely removed. As shown in Table 7, the None model serves as a baseline network consisting solely of DCT modules and transition layers. Compared to the None model, the Standard (DCTNet) model demonstrated improvements in multiple key metrics after incorporating the MSCA module. Specifically, ACC increased from 58.18% to 58.55%, PPV Macro improved from 58.66% to 61.54%, NPV Macro rose from 84.71% to 85.07% and the F1 Macro score also climbed from 58.19% to 58.32%. This consistent performance growth validates the effectiveness of the MSCA module, which enhances the model’s discriminative power by introducing a multi-frequency channel attention mechanism. This innovation enables the network to capture richer feature information while maintaining minimal computational overhead (with negligible changes in FLOPs and parameters), significantly boosting the model’s predictive capabilities. Therefore, in subsequent ablation experiments, DCTNet was used in the standard structure if not otherwise specified.
In this subsection, to investigate the effect of CoT block on the performance of DCTNet, we gradually replace the 3 × 3 convolution in the four stages of the DCTNet backbone (res2 → res3 → res4 → res5) with CoT block and compare its diagnostic performance. To ensure balance, the same experimental parameters and structures are chosen for the remaining configurations and the final results are shown in Table 8. From the table, the model achieves 57.43% accuracy (ACC) when using CoT blocks only in the final stage (res5). As more replacement stages are introduced, the model’s performance improves steadily. When all four 3x3 convolutional layers are fully replaced with CoT blocks, the model reaches optimal accuracy (58.55%) and F1 Macro (58.32%), while achieving the lowest computational cost (FLOPs: 2.22 G) and parameter size (Param: 6.08 M). So we choose to replace 3 × 3 convolutions in all stages in DCTNet. At the same time, we can see that increasing the replacement stage of CoT block improves the diagnostic performance with a slight decrease in FLOPs and number of parameters, proving the effectiveness of CoT block for DCTNet.
Furthermore, to evaluate the contribution of the DCT module itself, we conducted a DCT-off experiment where the DCT module was completely removed from the network while keeping all other components intact. As shown in Table 9, the DCT-off model achieved lower performance (ACC: 56.82%) compared to the full DCTNet (ACC: 58.55%). To compare the effectiveness of our hybrid approach, we also implemented two baselines: a transformer-only model (replacing all CNN components with transformer blocks) and a CNN-only model (replacing all transformer components with CNN blocks). As shown in Table 9, both baselines underperform the DCTNet, with the CNN-only model achieving 52.34% ACC and the transformer-only model achieving 55.67% ACC, while DCTNet achieves 58.55% ACC. This demonstrates that the combination of CNN and transformer architectures, along with the DCT module, is essential for optimal performance.
5. Discussion
In this paper, DCTNet is designed to diagnose cervical lesions in response to the problems existing in the current research field. DCTNet can effectively combine the neighboring contextual information and global contextual information, which improves the expression ability of the features and diagnostic performance. Table 5 and Figure 5 demonstrate that the diagnostic performance of DCTNet is generally better than the current assisted diagnosis methods and can provide effective assisted diagnosis for resource-poor areas.
In addition, Table 6 and Figure 6 demonstrate that the clinical performance of DCTNet can reach the level of advanced physicians, which is clinically important for the screening of cervical precancerous lesions. On the one hand, due to the trend of youthfulness and the number of cervical cancer patients increasing year by year, but the training of clinicians is time-consuming and at the same time, it needs to invest a large amount of medical funds, as well as take up the time and energy of high-level clinicians, increasing the pressure of physicians’ work. Second, the professional level of physicians at all levels varies and the diagnostic level of resource-poor physicians is difficult to meet the standardized standards and requirements. All these will lead to low screening efficiency and inevitable misdiagnosis and omission, DCTNet has excellent auxiliary diagnostic performance and is much faster and more efficient than clinicians, which can effectively alleviate the pressure on physicians in resource-poor areas, reduce unnecessary time occupation and at the same time, can play a standardized role in guiding junior physicians.
Despite the promising results of DCTNet, there are still areas for improvement. First, DCTNet’s performance, while reaching the level of senior physicians, has not yet achieved the anticipated expert-level diagnostic accuracy. Furthermore, enhancement is necessary to align DCTNet’s performance more closely with that of expert physicians. Second, the sample size of data used in this study was limited due to the difficulty of obtaining cancer-related clinical data in the field of cervical cancer. Future research will focus on increasing the data volume to improve the robustness of the findings.
Furthermore, the interpretability of DCTNet’s predictions has not been adequately discussed. Providing clear guidelines on how to interpret the model’s outputs and integrating interpretability features would enhance its clinical utility. Ensuring that clinicians can effectively understand and trust the model’s predictions is essential for its practical application in real-world settings. Future work will also focus on developing and incorporating interpretability features to make DCTNet’s predictions more transparent and actionable for clinical use.
6.Conclusions
Aiming at the problems of previous cervical assisted diagnosis studies, this paper designs DCTNet to diagnose cervical lesions by combining the ability of a transformer to capture global contextual information with the ability of a CNN to capture neighboring local contextual information and the results show that DCTNet outperforms current other methods, has excellent performance in assisting diagnosis and far exceeds clinicians in terms of speed and efficiency. Although there are still some limitations, it can effectively alleviate the pressure on physicians in resource-poor areas, reduce the unnecessary occupation of physicians’ time and at the same time, it can serve as a standardized guide for junior physicians.
Contribution statement
Ping Li: Formal analysis, Investigation, Methodology, writing-original draft, writing-review and editing. Tianxiang Xu: Formal analysis, investigation, writing-original draft. Yao Liu: Methodology, writing-original draft, writing-review and editing. Yuling Fan: Methodology. YaTing Hong: Project administration, writing -review and editing. Jing-Ming Guo: Project administration, writing -review and editing. YuChun Lv: Project administration, writing-review and editing.
Ping Li, Tianxiang Xu and Yao Liu authors, have contributed equally to this work.
Ethics statement
This study involving human participants was reviewed and approved by the Ethics Committee of Quanzhou First Hospital (Approval Nos.: Quan-Yi-Lun [2021] 280 and Quan-Yi-Lun [2021] 281). All procedures performed in this study were in accordance with the ethical standards of the Declaration of Helsinki. Written informed consent was obtained from all individual participants prior to their enrollment.